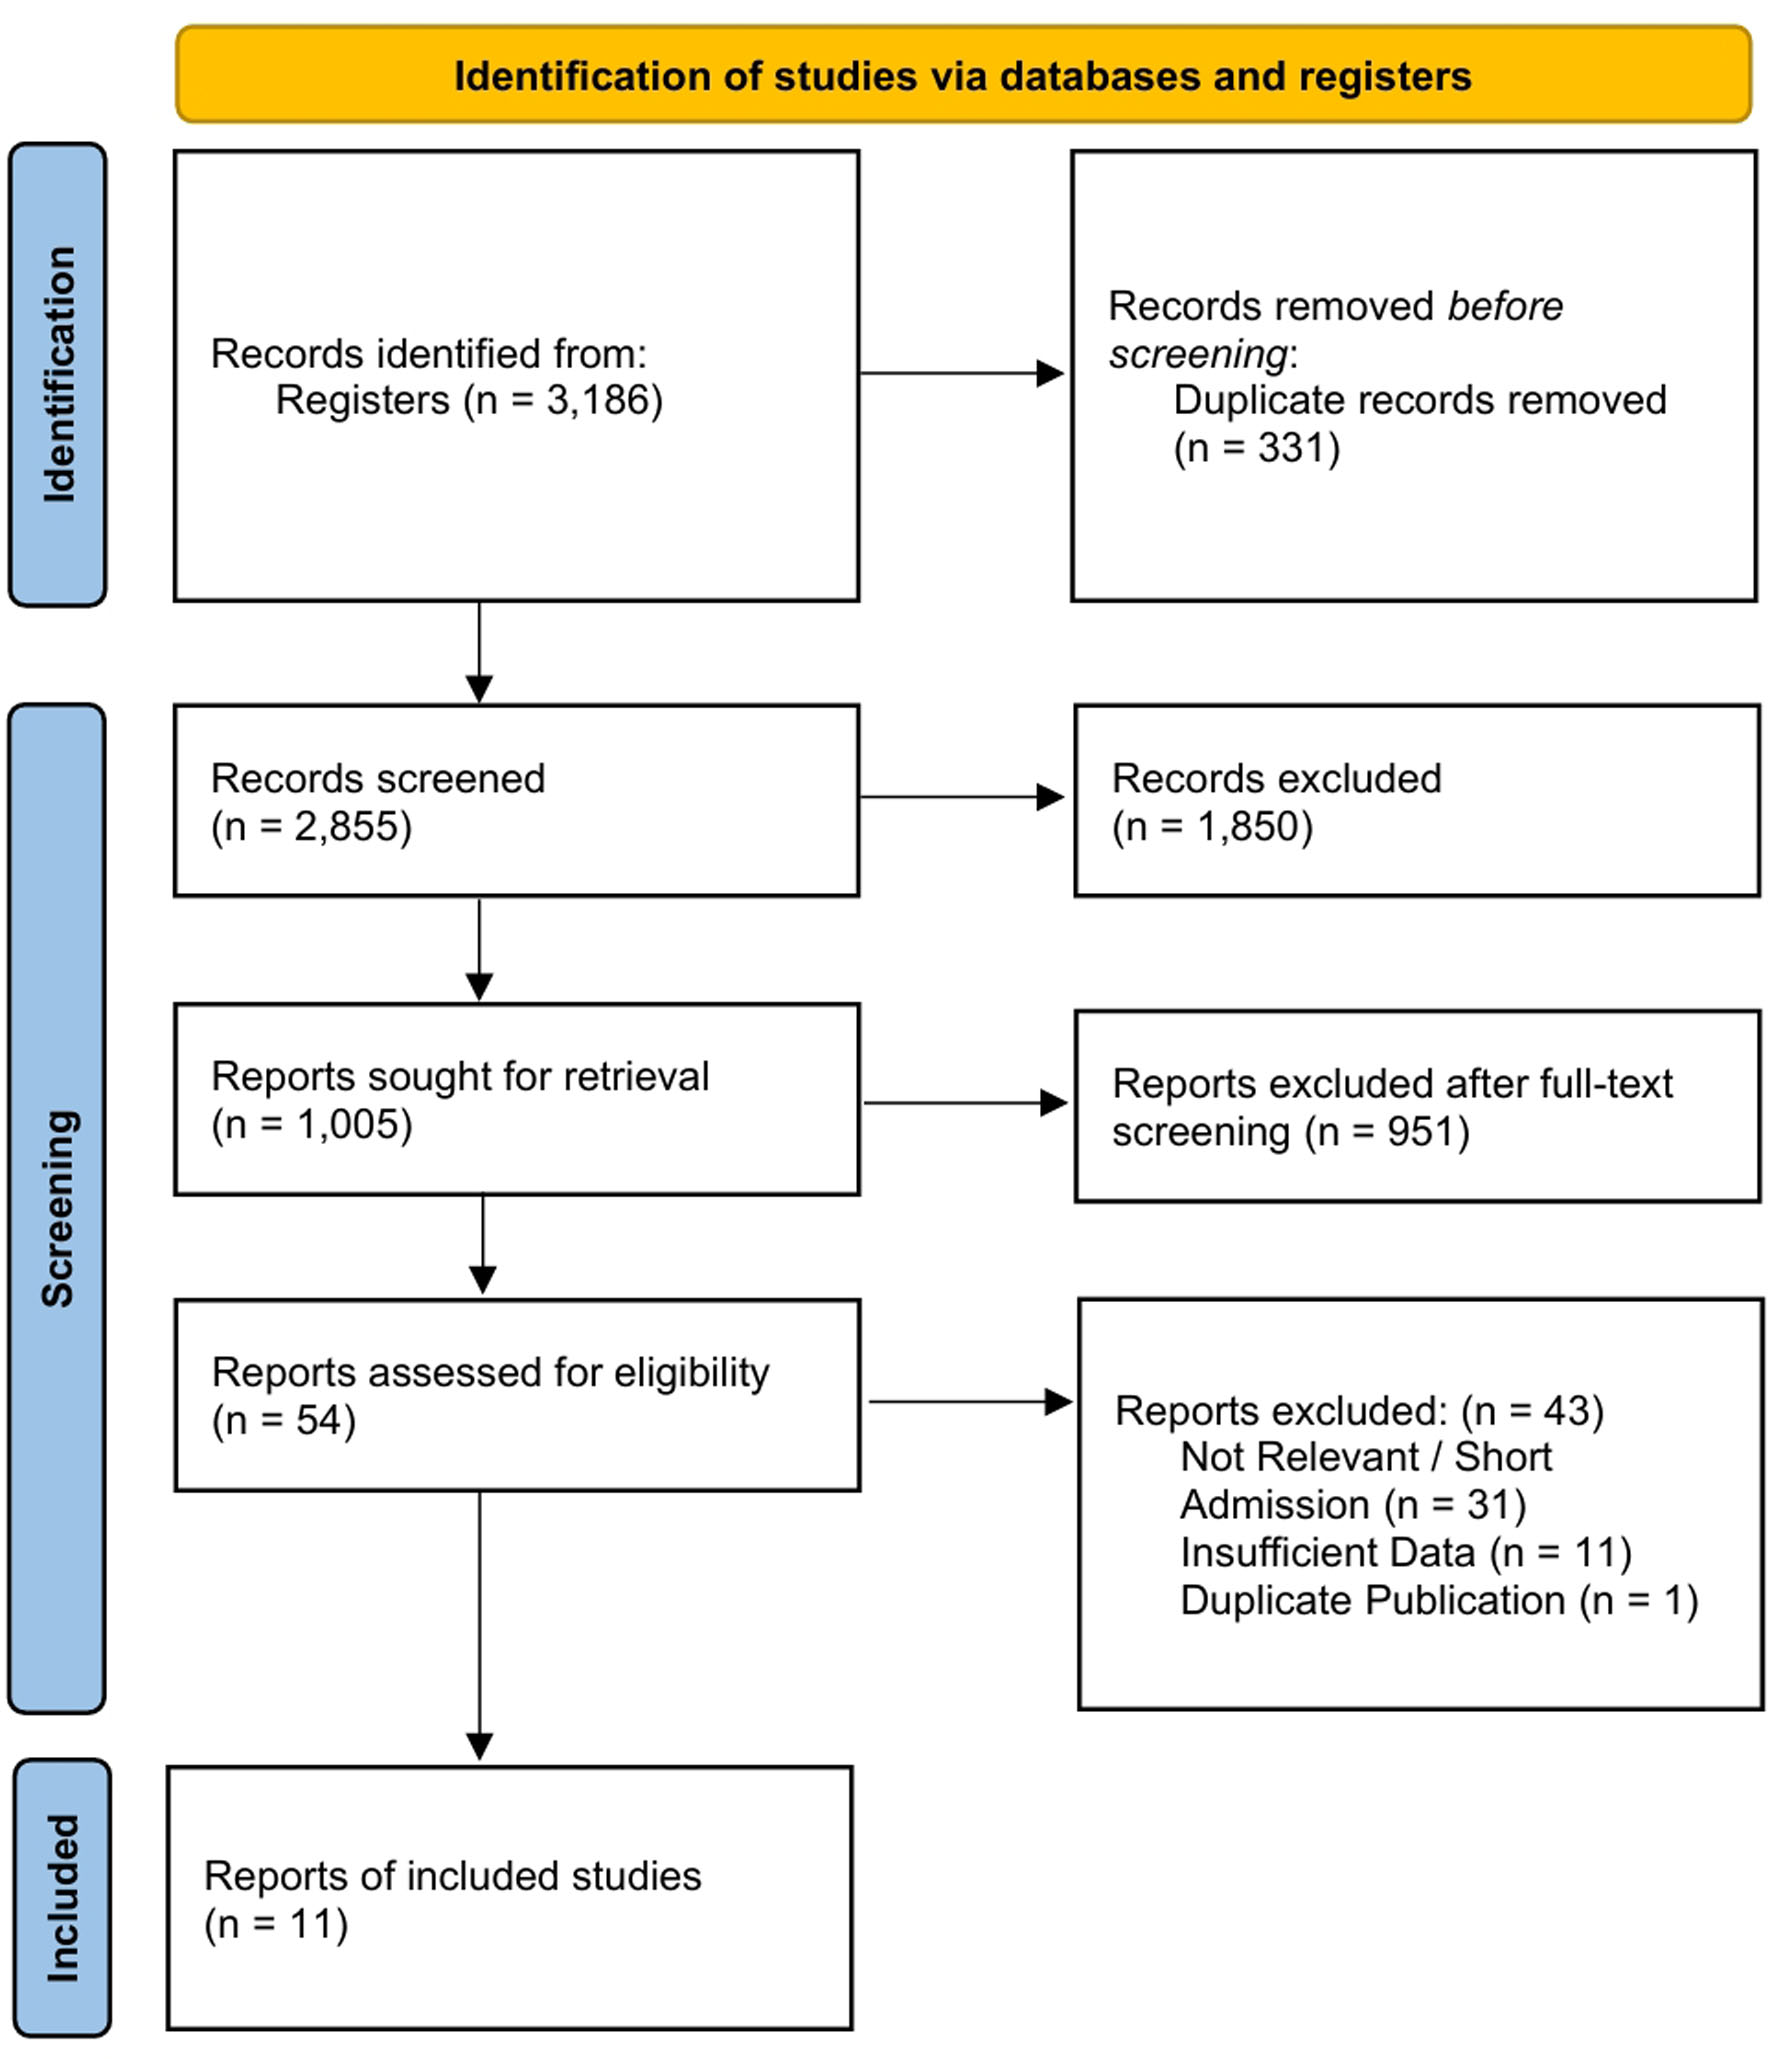
↓ Figure 1. PRISMA 2020 flow diagram.
| Journal of Clinical Medicine Research, ISSN 1918-3003 print, 1918-3011 online, Open Access |
| Article copyright, the authors; Journal compilation copyright, J Clin Med Res and Elmer Press Inc |
| Journal website https://jocmr.elmerjournals.com |
Original Article
Volume 18, Number 10, October 2026, pages 704-720
Comparative Efficacy and Safety of Corticosteroids vs. No Corticosteroids in Septic Shock Intensive Care Unit Patients: A Systematic Review and Meta-Analysis
Figures
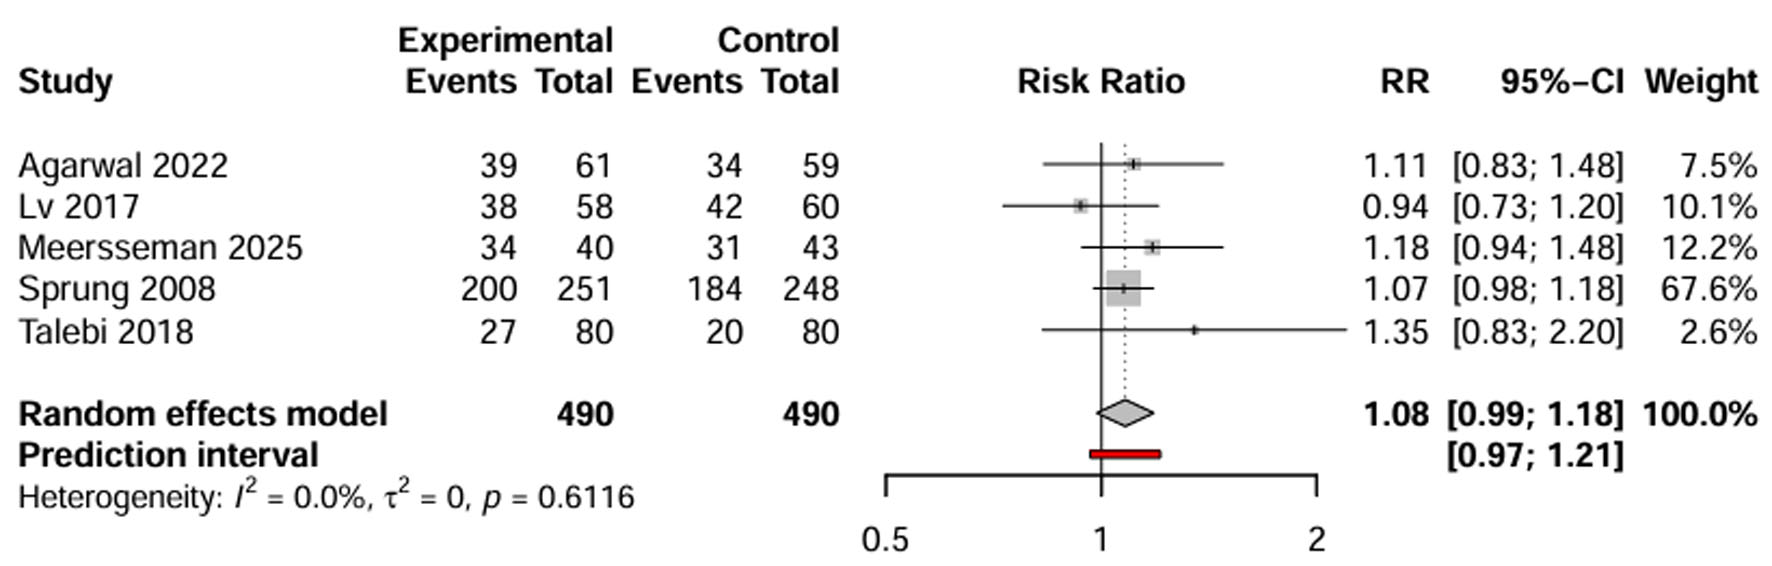
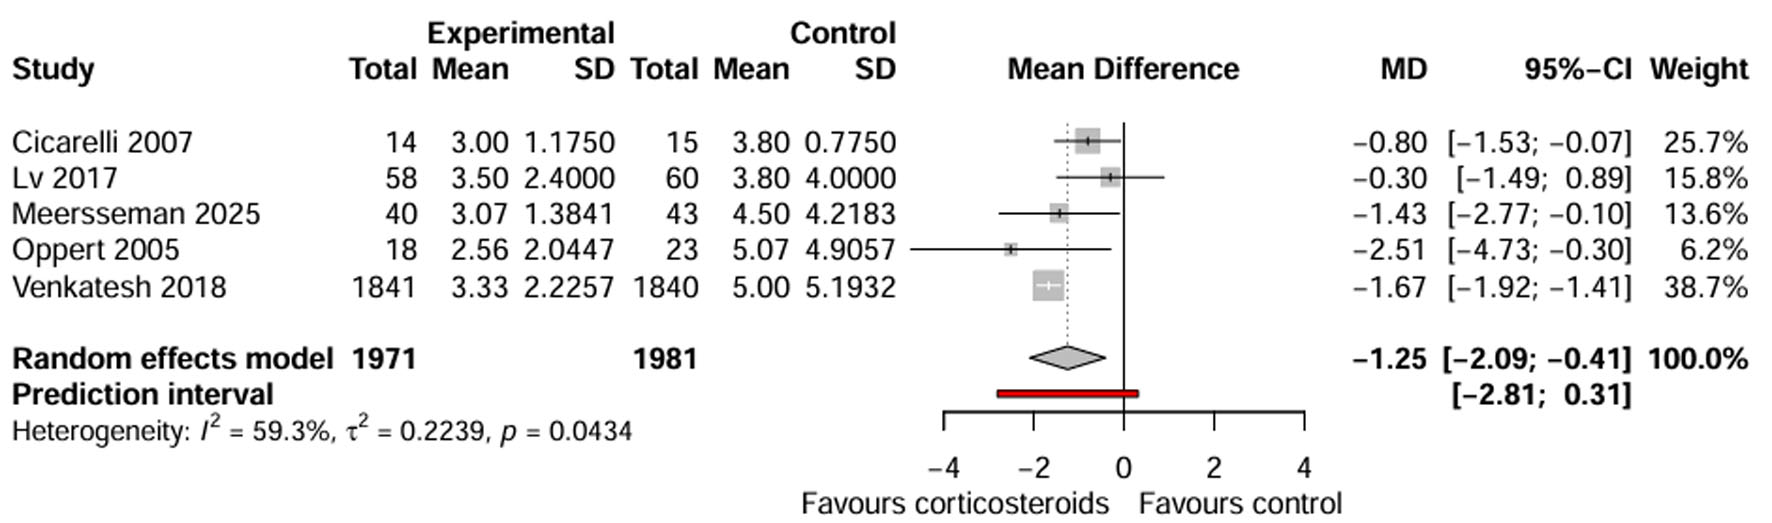
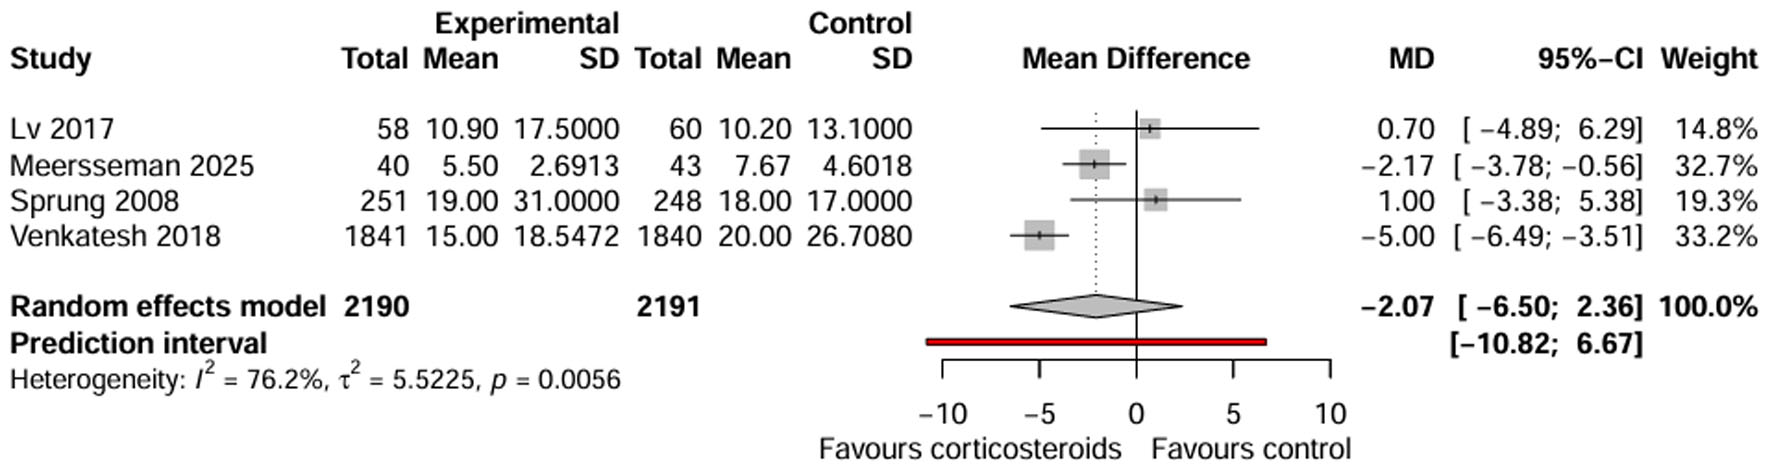
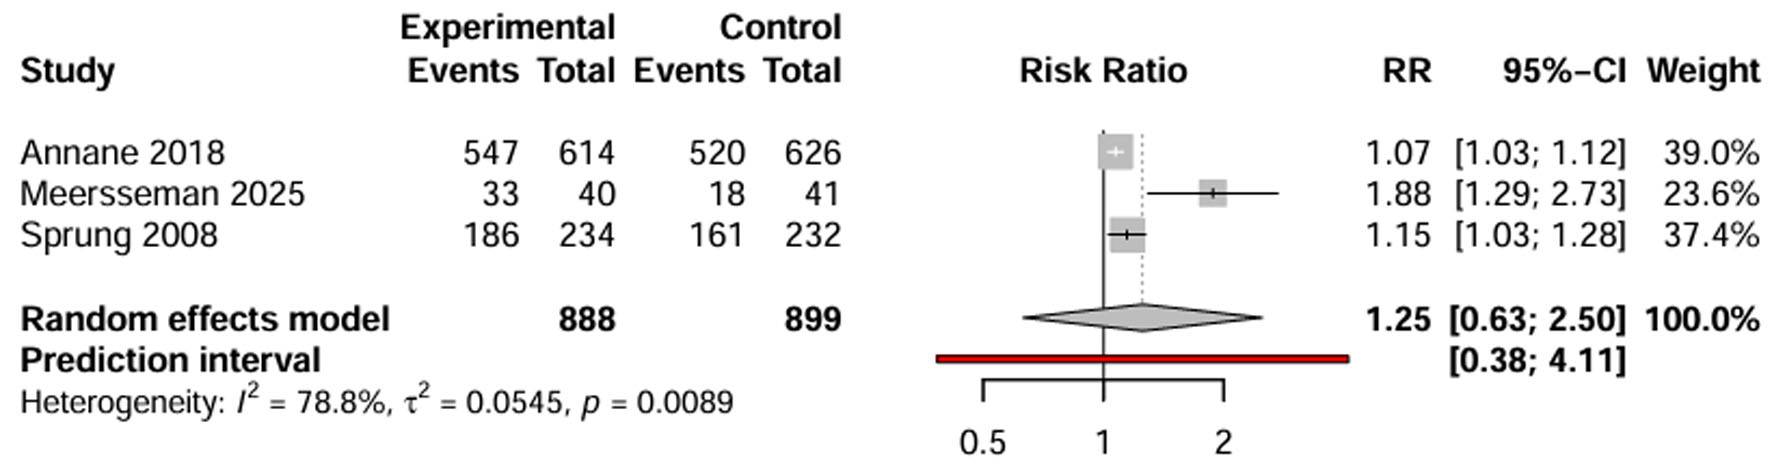
Tables
| Study | Author, year | Country | Population/setting | Intervention (drug, dose, duration) | Comparator | Total N (intervention/control) |
|---|---|---|---|---|---|---|
| aADRENAL [34] randomized 1,853 intervention/1,860 control (total 3,713); 1,841/1,840 were analyzed for 28-day mortality. ACTH: adrenocorticotropic hormone; ICU: intensive care unit; IV: intravenous. | ||||||
| [24] | Agarwal, 2022 | India | Geriatric patients (> 60 years) with septic shock in ICU | Hydrocortisone: 200 mg/day IV in four divided doses, tapered after shock reversal | Standard therapy | 120 (61/59) |
| [25] | Annane, 2002 | France | Adults with septic shock (ACTH non-responders & responders) | Hydrocortisone 50 mg IV q6h + fludrocortisone 50 µg/day enteral for 7 days | Placebo | 299 (150/149) |
| [26] | Annane, 2018 | France | Adults with septic shock (APROCCHSS trial) | Hydrocortisone 50 mg IV q6h + fludrocortisone 50 µg/day enteral for 7 days | Placebo | 1241 (614/627) |
| [27] | Cicarelli, 2007 | Brazil | Adults with septic shock | Dexamethasone: 0.2 mg/kg IV, three doses at 36 h intervals | Placebo | 29 (14/15) |
| [28] | Gordon, 2014 | UK | Adults with septic shock (VANISH pilot) | Vasopressin + hydrocortisone 50 mg IV q6h | Vasopressin + placebo | 61 (31/30) |
| [29] | Lv, 2017 | China | Adults with septic shock (within 6 h of onset) | Hydrocortisone: 200 mg/day continuous infusion for 6 days, then tapered | Placebo | 118 (58/60) |
| [30] | Meersseman, 2025 | Europe | Cirrhotic patients with septic shock | Hydrocortisone: 100 mg bolus + 200 mg/day continuous infusion for ≥ 3 days | Placebo | 83 (40/43) |
| [31] | Oppert, 2005 | Germany | Adults with early hyperdynamic septic shock | Hydrocortisone: 50 mg bolus + 0.18 mg/kg/h continuous infusion, then tapered | Placebo | 41 (18/23) |
| [32] | Sprung, 2008 | Int'l | Adults with septic shock (CORTICUS trial) | Hydrocortisone: 50 mg IV q6h for 5 days, then tapered | Placebo | 499 (251/248) |
| [33] | Talebi Doluee, 2018 | Iran | Adults with refractory septic shock | Hydrocortisone: 50 mg IV q6h for 7 days | Placebo | 160 (80/80) |
| [34] | Venkatesh, 2018 | Int'l | Adults with septic shock on mechanical ventilation (ADRENAL) | Hydrocortisone: 200 mg/day continuous infusion for 7 days | Placebo | 3,713 (1,853/1,860)a |
| Subgroup | k | Pooled RR (95% CI) | I2/τ2 | Qbetween | P |
|---|---|---|---|---|---|
| The em-dash (—) denotes a parameter not estimable owing to k = 1. aThe early-initiation subgroup (k = 2) [29, 31] yields an uninformative estimate: the 95% CI (0.09–14.00) spans two orders of magnitude owing to the extreme between-study standard error and should be regarded as hypothesis-generating only, not as evidence of equivalence. k: number of trials within subgroup; CI: confidence interval; I2: inconsistency statistic; Qbetween: Cochran’s Q test for subgroup differences; RR: risk ratio; τ2: between-study variance. | |||||
| Regimen | 6.41 | 0.041 | |||
| Hydrocortisone alone | 8 | 0.93 (0.86–1.01) | 0.0%/0 | — | — |
| Hydrocortisone + fludrocortisone | 2 | 0.88 (0.72–1.07) | 0.0%/0 | — | — |
| Dexamethasone | 1 | 0.63 (0.35–1.12) | — | — | — |
| Population | 0.14 | 0.986 | |||
| General adult ICU | 8 | 0.91 (0.85–0.99) | 0.0%/0 | — | — |
| Geriatric (> 60 years) | 1 | 0.85 (0.54–1.33) | — | — | — |
| Cirrhotic | 1 | 0.89 (0.51–1.55) | — | — | — |
| Refractory shock | 1 | 0.93 (0.76–1.14) | — | — | — |
| Immune status | 0.01 | 0.911 | |||
| Immunocompetent | 10 | 0.91 (0.86–0.97) | 0.0%/0 | — | — |
| Immunocompromised | 1 | 0.89 (0.51–1.55) | — | — | — |
| Timing of initiation | 0.83 | 0.362 | |||
| Standard/unspecified | 9 | 0.91 (0.86–0.96) | 0.0%/0 | — | — |
| Early (< 6 h or hyperdynamic) | 2 | 1.09 (0.09–14.00)a | 0.0%/0 | — | — |
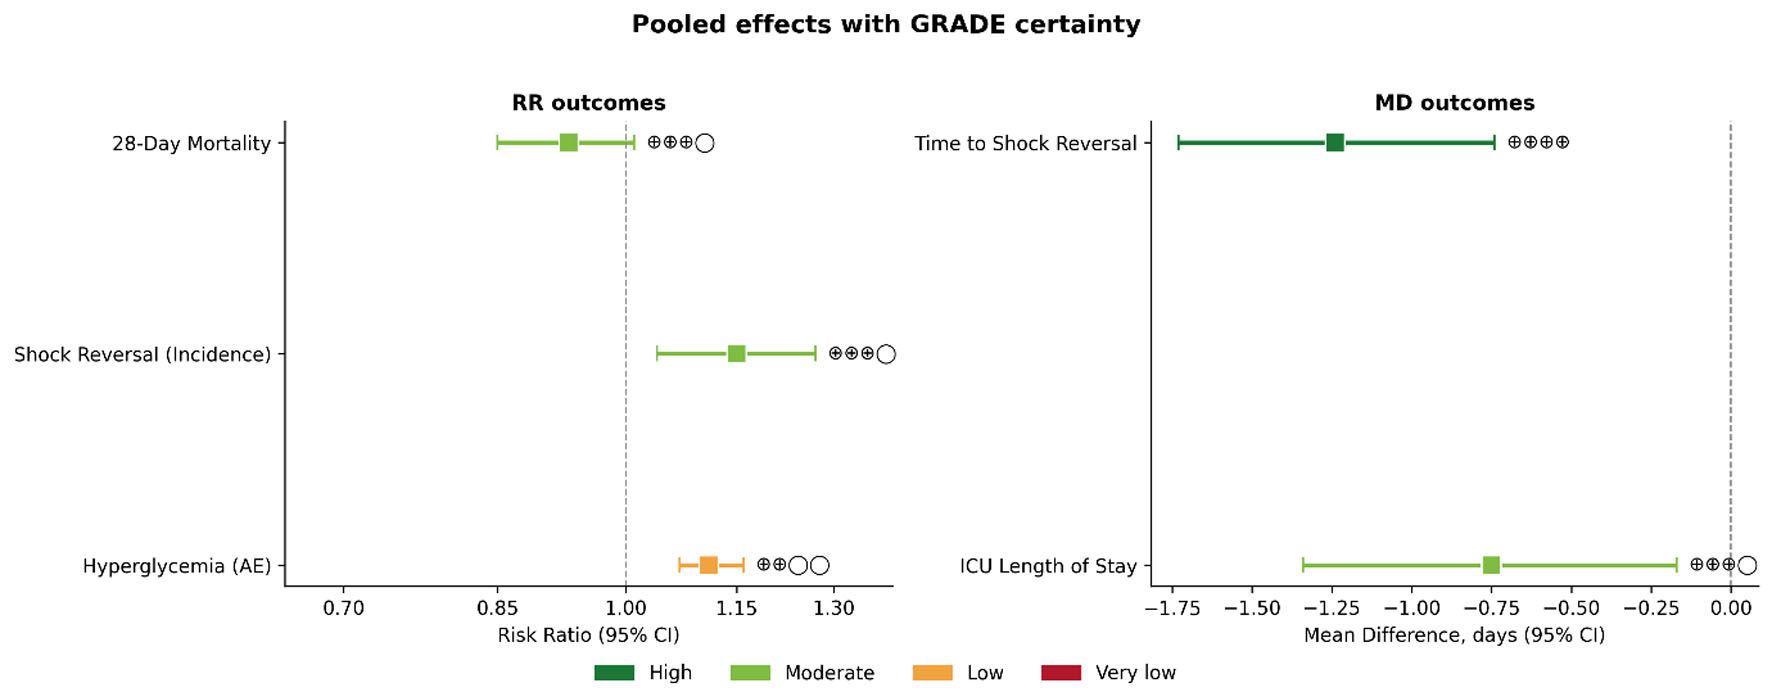
| Outcome | Studies (patients) | Pooled effect (95% CI) | Absolute effect | Certainty (GRADE) |
|---|---|---|---|---|
| aImprecision: although the 95% CI excluded the null, the absolute risk reduction did not meet the optimal information size threshold for a high-certainty conclusion. bRisk of bias: substantial contribution from trials at high or some-concerns RoB on a process-of-care outcome susceptible to clinician unblinding. cNo serious concerns; SMD sensitivity analysis confirmed scale-robust effect (SMD −0.41, 95% CI −0.51 to −0.32; I2 = 10.8%). dInconsistency (I2 = 76.2%) and indirectness (ICU discharge influenced by step-down logistics). eInconsistency (varied operational definitions of hyperglycemia across trials) and indirectness (biochemical surrogate for patient-centered metabolic harm). CI: confidence interval; ICU: intensive care unit; MD: mean difference; OIS: optimal information size; PI: prediction interval; RCTs: randomized controlled trials; RR: risk ratio; SMD: standardized mean difference. | ||||
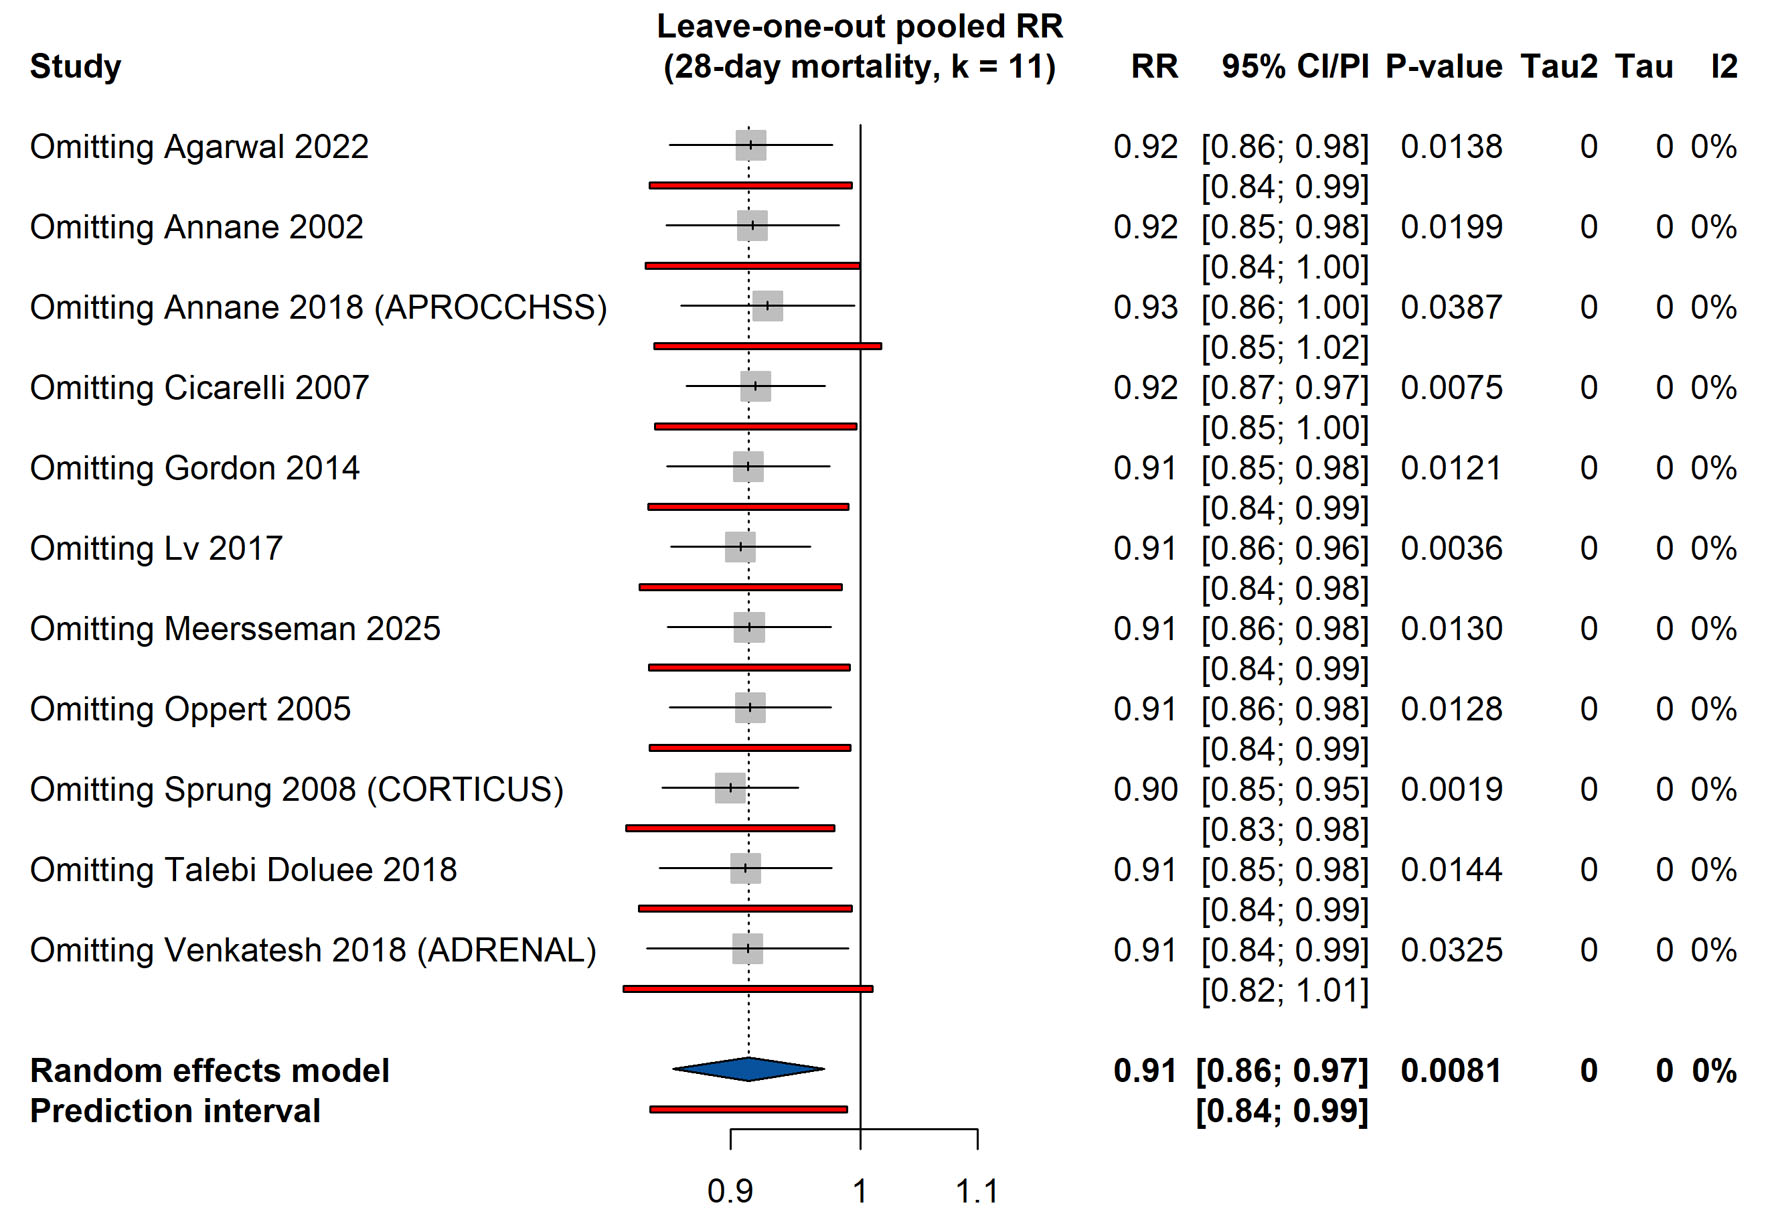
| 28-day all-cause mortality | 11 RCTs (6,332) | RR 0.91 (0.86–0.97) | 27 fewer deaths per 1,000 (10 to 44 fewer) | ⊕⊕⊕◯ Moderatea |
| Shock reversal (incidence) | 5 RCTs (980) | RR 1.08 (0.99–1.19) | 51 more per 1,000 (10 fewer to 117 more) | ⊕⊕⊕◯ Moderateb |
| Time to shock reversal | 5 RCTs (3,952) | MD −1.25 days (−2.09 to −0.41) | 1.25 fewer days on vasopressors | ⊕⊕⊕⊕ Highc |
| ICU length of stay | 4 RCTs (4,381) | MD −2.07 days (−6.50 to 2.36) | 2.07 fewer days in the ICU (95% CI crosses null) | ⊕⊕◯◯ Lowd |
| Hyperglycemia (adverse event) | 3 RCTs (1,787) | RR 1.26 (0.63–2.50) | Wide PI (0.38–4.11); each contributing trial individually showed excess | ⊕⊕◯◯ Lowe |