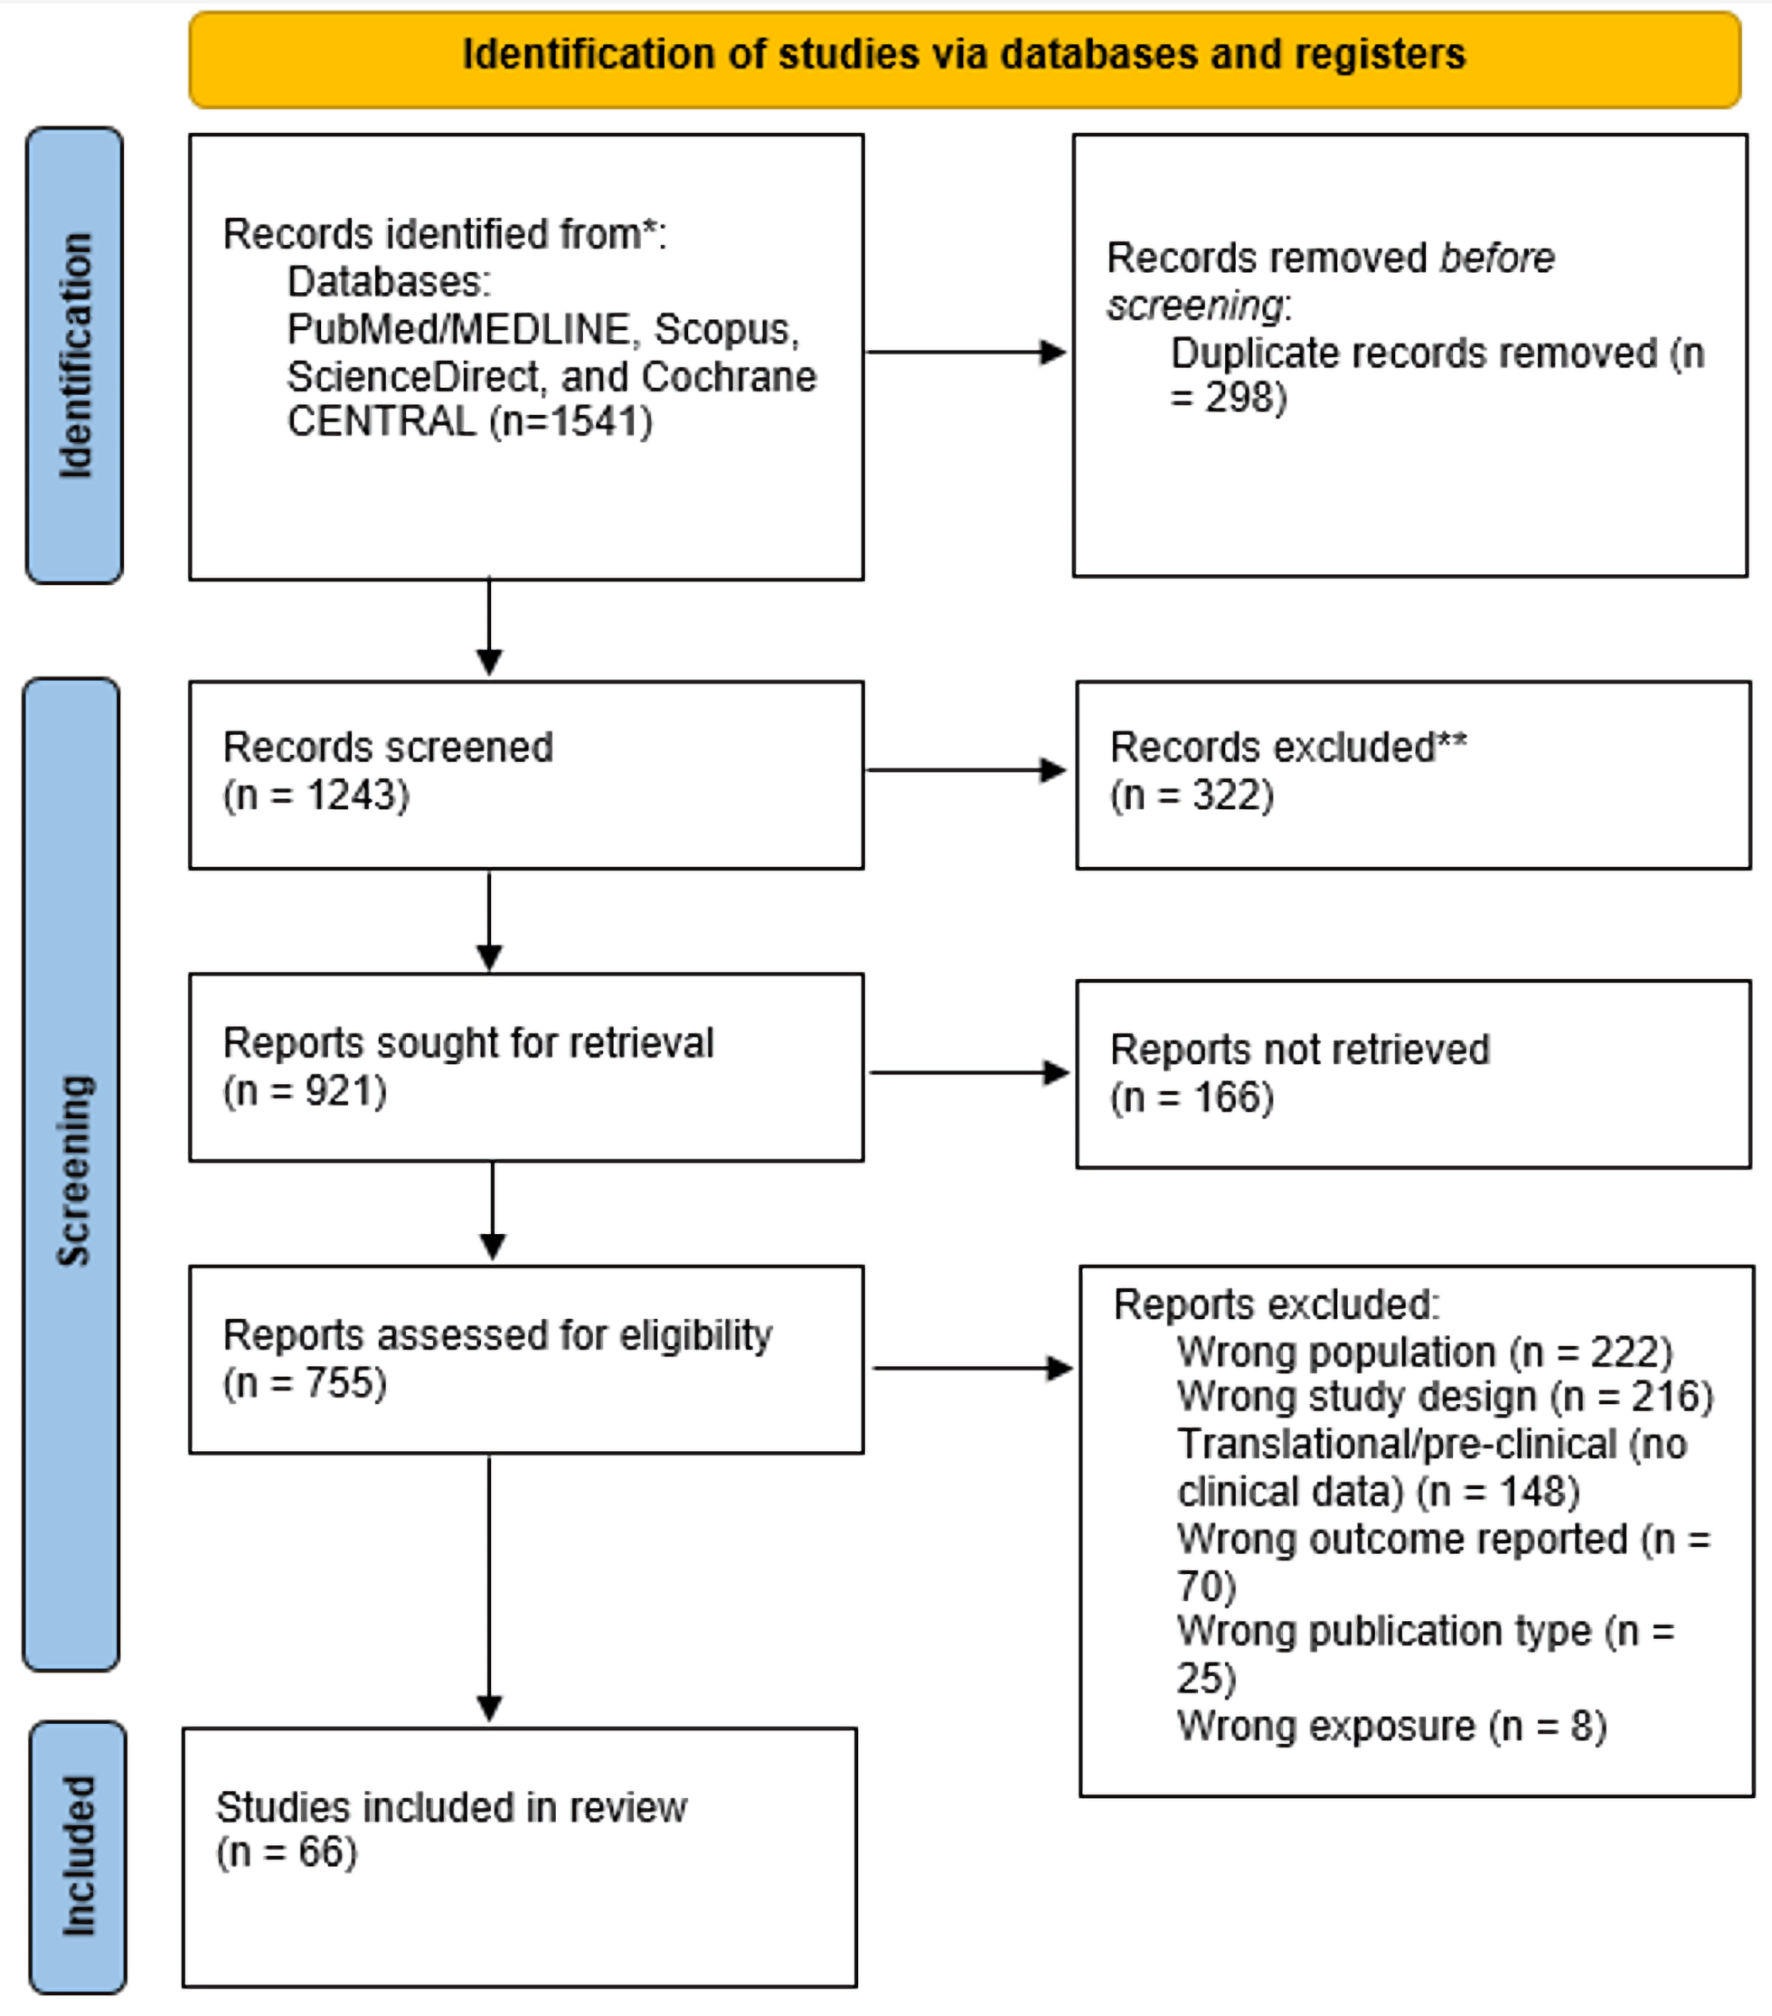
↓ Figure 1. PRISMA flow diagram. Databases (PubMed/MEDLINE, Scopus, ScienceDirect, Cochrane CENTRAL) were last searched in August 2026. PRISMA: Preferred Reporting Items for Systematic Reviews and Meta-Analyses.
| Journal of Clinical Medicine Research, ISSN 1918-3003 print, 1918-3011 online, Open Access |
| Article copyright, the authors; Journal compilation copyright, J Clin Med Res and Elmer Press Inc |
| Journal website https://jocmr.elmerjournals.com |
Review
Volume 18, Number 11, November 2026, pages 795-814
Immune-Mediated Necrotizing Myopathy Across the Age, Autoantibody, Phenotype, Treatment, and Outcome Spectrum: A Systematic Review
Figure
Tables
| Category | N | % |
|---|---|---|
| Adult | 52 | 78.8% |
| Pediatric (onset/age < 18 years) | 8 | 12.1% |
| Mixed pediatric and adult | 4 | 6.1% |
| Not reported | 2 | 3.0% |
| Category | N | % |
|---|---|---|
| Anti-HMGCR: anti-3-hydroxy-3-methylglutaryl-coenzyme A reductase; anti-SRP: anti-signal recognition particle. | ||
| Anti-HMGCR reported (any mention) | 40 | 60.6% |
| Anti-SRP reported (any mention) | 20 | 30.3% |
| Both anti-HMGCR and anti-SRP addressed in the same report | 10 | 15.2% |
| Seronegative disease specifically reported | 8 | 12.1% |
| Antibody status not stratified/not specified by subtype | 12 | 18.2% |
| Category | N | % |
|---|---|---|
| CAR-T: chimeric antigen receptor T-cell; PCSK9i: proprotein convertase subtilisin/kexin type 9 inhibitor; FcRn: neonatal Fc receptor. | ||
| Corticosteroids (any regimen) | 40 | 60.6% |
| Intravenous immunoglobulin (IVIG) | 27 | 40.9% |
| Methotrexate | 15 | 22.7% |
| Azathioprine | 12 | 18.2% |
| Rituximab | 10 | 15.2% |
| Mycophenolate mofetil | 9 | 13.6% |
| Statin exposure documented/discussed | 20 | 30.3% |
| Cell-based/complement/FcRn-targeted therapy (CAR-T, zilucoplan, efgartigimod, PCSK9i, tocilizumab, belimumab) | 6 | 9.1% |
| Death, fatal outcome, or mortality specifically reported | 3 | 4.5% |
| Study/group | N (participants, or reports for grouped rows) | Tool | Judgment |
|---|---|---|---|
| RoB 2: risk-of-bias tool for randomized trials; ROBINS-I: Risk of Bias in Non-Randomized Studies of Interventions; JBI: Joanna Briggs Institute; RCT: randomized controlled trial. | |||
| Mammen et al, 2023 [34] (zilucoplan RCT) | 27 | RoB 2 | Low risk: computerized 1:1 randomization, double-blind, pre-specified endpoints (NCT04025632). Negative primary endpoint is informative, not a source of bias. |
| Chen et al, 2025 [35] | 216 | ROBINS-I | Moderate: multi-center retrospective; limited confounder adjustment; outcome not blinded. |
| Wang et al, 2025 [24] (pediatric) | 55 | ROBINS-I | Moderate–serious: single-center registry; selection and reporting bias possible. |
| Xiong et al, 2021 [23] (rituximab) | 34 | JBI (pooled case review) | Moderate–serious: pooled published cases; unblinded and heterogeneous response assessment; publication bias possible. Counted within the eight case series/pooled reviews. |
| Martinez-Lopez et al, 2023 [32] | 24 | ROBINS-I (abstract only) | Moderate–serious (provisional, abstract-level): limited methodological detail; residual confounding. |
| Tsokkos et al, 2026 [36] | 36 | ROBINS-I | Moderate: national referral series; serology incomplete in early cases. |
| Huo et al, 2026 [37] | 28 | ROBINS-I | Moderate: treatment-naive consecutive sample; cross-sectional only. |
| Chung et al, 2021 [13] | 108 | ROBINS-I | Moderate: multi-center clinicoserologic reclassification; tertiary-center selection. |
| Sumi et al, 2025 [38], Kurashige et al, 2024 [39], Caballero et al, 2024 [31], Dinh et al, 2026 [29] | 13–148 | ROBINS-I/JBI | Moderate–serious: small single-center series focused on cardiac, skin, lipids or ethnicity. |
| Other cohort/registry studies | 14 reports | ROBINS-I | Predominantly moderate–serious: single-center retrospective; limited confounding adjustment; short follow-up; several abstract-only (provisional). |
| Case series (≥ 3 patients) | 8 reports | JBI case series | Adequate core reporting (demographics, diagnosis, treatment, outcome); consecutive inclusion rarely confirmed; selection bias possible. |
| Case reports (1–2 patients) | 31 reports | JBI case report | Core elements present; adverse events and long-term follow-up inconsistent; clinical signal only. |
| Narrative reviews | 2 reports | Not graded | Contextual only; excluded from quantitative synthesis. |
| Study | Country | Design | Population | N | Antibody | Key data/phenotype |
|---|---|---|---|---|---|---|
| HMGCR: 3-hydroxy-3-methylglutaryl-coenzyme A reductase; SRP: signal recognition particle; CAPN3: calpain-3; C5b-9: membrane attack complex; IVIG: intravenous immunoglobulin; CK: creatine kinase; CPK: creatine phosphokinase; MMF: mycophenolate mofetil; SMR: standardized mortality ratio; DFR: drug-free remission; GC: glucocorticoid(s); RTX: rituximab; AZA: azathioprine; MTX: methotrexate; TEAEs: treatment-emergent adverse events; MSAs: myositis-specific antibodies; ILD: interstitial lung disease; PAH: pulmonary arterial hypertension; NSTEMI: non-ST-elevation myocardial infarction; LGMD: limb-girdle muscular dystrophy; ICI: immune checkpoint inhibitor; CTD: connective tissue disease; NSIP: nonspecific interstitial pneumonia; UIP: usual interstitial pneumonia; IBM: inclusion body myositis; JDM: juvenile dermatomyositis; FSHD: facioscapulohumeral muscular dystrophy; NA: Native American; PCSK9i: proprotein convertase subtilisin/kexin type 9 inhibitor; CAR-T: chimeric antigen receptor T-cell therapy; hs-TnT: high-sensitivity troponin T; ECG: electrocardiogram; HF: heart failure; TC: total cholesterol; LDL: low-density lipoprotein; AIP: atherogenic index of plasma; CRS: cytokine release syndrome; ICANS: immune effector cell-associated neurotoxicity syndrome; F: female; M: male; IL: interleukin; IFN-γ: interferon-gamma; Ig: immunoglobulin; NK: natural killer; IIM: idiopathic inflammatory myopathy; IMNM: immune-mediated necrotizing myopathy; NR: not reported; RCT: randomized controlled trial; MRI: magnetic resonance imaging. | ||||||
| Villanova et al, 2018 [40] (abstract) | Italy | Case report | Pediatric (onset age 11; 20 years at report) | 1 | HMGCR | 20-year-old, onset age 11; anti-HMGCR 177 U/mL; CAPN3 reduction and mitochondrial changes on biopsy; sarcolemmal C5b-9 in few fibers; partial response to steroids + IVIG |
| Skiauteryte et al, 2021 [41] (abstract) | Lithuania | Case report | Adult | 1 | HMGCR | 66-year-old male, statin-induced, plasmapheresis + steroids |
| Pongtarakulpanit et al, 2025 [42] (abstract) | USA | Cohort (registry) | Adult | 440 | Mixed IIM (IMNM subset) | N = 440 IIM (IMNM n = 45); overall remission 28.4%; IMNM remission 26.7% (12/45) |
| Chen et al. [35] | China | Cohort (retrospective, mortality) | Adult | 1,854 | Mixed IIM (IMNM subset) | N = 1,854 IIM (IMNM n = 216: HMGCR 28.2%, SRP 51.4%, seroneg 20.4%); IMNM SMR 2.74; anti-SRP SMR 4.12; lower DFR in IMNM |
| Maher et al, 2025 [43] | Ireland | Case report | Adult | 1 | HMGCR | 62-year-old man; statin after MI; coexisting pheochromocytoma; IVIG and methylprednisolone pulse, then oral steroids + MMF; full strength regained after adrenalectomy and weaning of immunosuppression |
| Aziz et al, 2025 [28] (abstract) | UK | Cohort (retrospective) | Adult | 31 | HMGCR (7/31) | N = 31; anti-HMGCR 7/31 (22.6%) all statin-exposed; 6/7 (85.7%) clinical IMNM phenotype |
| Navarro Perez et al, 2019 [44] | Spain | Case report | Adult | 1 | HMGCR | 63-year-old woman; rosuvastatin; CK 1,932–2,195; prednisone 1 mg/kg + azathioprine; CK 72 IU/L at 10 months |
| Xiao et al, 2024 [45] | China | Cohort (mechanistic/RNAseq) | Adult | 174 | Mixed IIM (IMNM subset) | N = 174 IIM + 19 controls (RNA-seq and proteomics); intron retention profiles differ by subtype; YBX1/HSPA2 changes in DM and IMNM; SRP14 intron retention associated with anti-SRP |
| Sridhar et al, 2025 [30] | India | Cohort (ambispective, imaging) | Mixed | 125 | Mixed IIM (IMNM subset) | MRI in 125 IIM (DM, IMNM, OM, seronegative groups); IMNM: grade 4–5 edema in rectus femoris/semimembranosus in 52.1%, peronei spared in 78.2%, fatty replacement more pronounced |
| Brannick et al, 2017 [46] (abstract) | USA | Case report | Adult | 1 | HMGCR | 61-year-old man; atorvastatin 80 mg; CK 32,000; anti-HMGCR 35 U; prednisone, azathioprine, IVIG; CK normalized at 4 months; PCSK9 inhibitor (alirocumab) for lipid control |
| Zhu et al, 2025 [47] (abstract) | China | Case series | NR | 5 | HMGCR | 5 patients; persistent truncal violaceous/erythematous plaques; rash preceded muscle symptoms in 4/5 (median 3 years); improved with immunosuppression, not with steroids alone; Huashan Hospital |
| Oleszkiewicz et al, 2024 [48] (abstract) | Poland | Case series | Adult | 14 | HMGCR 9, SRP 3, NR 2 | 13 women/1 man; 8 statin-exposed; no seronegative cases; GCS ± AZA/MMF/MTX/IVIG/RTX; all improved initially; 1 severe disability at 10 years |
| de la Fuente Penaloza et al, 2024 [49] | Chile | Case series | Adult | 3 | HMGCR | 3 women aged 47–78, all statin-exposed (rosuvastatin × 2, atorvastatin × 1); CK 5,669–10,622; prednisone ± MTX, then IVIG, methylprednisolone, cyclophosphamide/cyclosporine on relapse; one with skin plaque |
| Sun et al, 2026 [50] (abstract) | USA | Case report | Adult | 1 | HMGCR | 67-year-old woman; hs-troponin > 1,200, CK 16,925; ECG, echo, cardiac MRI reassuring; anti-HMGCR 174 U/mL; statin resumed before onset; IVIG + steroids |
| Boulus et al et al, 2025 [51] (Abstract) | USA | Case report | Adult | 1 | Seronegative | 42-year-old, Coxsackie B myocarditis + seronegative IMNM; treated with IV prednisone, IVIG, rituximab and plasmapheresis; background myasthenia gravis |
| Volkov et al, 2024 [52] | USA (multi-site trial) | Case report (trial substudy) | Adult | 1 | SRP | CD19 CAR-T: First IMNM subject: no CRS/ICANS; B-cell aplasia d15; CK decreased, strength improved; SRP/Ro52 Abs decreased |
| Halberg et al, 2025, [53] | USA | Case report | Adult | 1 | HMGCR | 63-year-old man; atorvastatin; prior biopsy active and chronic necrotizing myopathy; HMGCR IgG markedly elevated; systemic corticosteroids + IVIG, then monthly IVIG and prednisone taper |
| Sumi et al, 2025 [38] | Japan | Cohort (retrospective) | Adult | 13 | Not by subtype | N = 13; all elevated TnT; 76.9% ECG/echo (abnormal); 23.1% acute HF (1 death); anti-Kv1.4+ in 83.3% |
| Molinero et al, 2025 [54] (abstract) | Spain | Cohort (retrospective) | Adult | 45 | HMGCR | N = 45 anti-HMGCR; statin stop significantly raised TC/LDL; sex differences in lipids; AIP as risk tool |
| Martinez-Lopez et al, 2023, [32] (abstract) | Spain/Poland/Sweden (multicentric) | Cohort (retrospective, comparative) | Adult | 24 | HMGCR | GC-free IVIG regimen (n = 5) vs standard GC (n = 19); remission or low activity 21/24 (87.5%), all 5 GC-free; 3/19 GC-treated not in remission; overall IVIG 75%, MTX 75%, RTX 16.7%, AZA 12.5% |
| Wang et al, 2025 [24] | China | Cohort (retrospective) | Pediatric | 55 | HMGCR 61.8%, SRP 20.0%, seronegative 18.2% | N = 55 (38 F/17 M, median age 7 years); HMGCR 61.8%, SRP 20.0%, seronegative 18.2%; 39 followed 6 months: all high-dose corticosteroids, 34 multiple immunotherapies (IVIG 26, MTX 17, RTX 12, tacrolimus 9, AZA 1); complete/partial remission 18/39 (46.2%) |
| Quasem et al, 2026 [55] | USA | Case report | Adult | 1 | HMGCR | 69-year-old man; atorvastatin 3 weeks; anti-HMGCR 459; hs-TnT rise prompted NSTEMI workup; pulse methylprednisolone, IVIG and methotrexate |
| Mammen et al, 2023 [34] | Multinational (15 sites, four countries) | RCT (phase 2) | Adult | 27 | HMGCR or SRP | N = 27 (zilucoplan 12, placebo 15), 8 weeks; primary CK endpoint not met (P = 0.46); no serious TEAEs on zilucoplan; background glucocorticoids, immunosuppressants and IVIG continued |
| Luo et al, 2018 [56] (abstract) | China | Cohort (retrospective) | Mixed (onset as young as 3–6 years) | 161 | Mixed IIM (IMNM n = 7; SRP 71.4% of IMNM) | PM 70, DM 81, IMNM 7, IBM 3; MSAs tested in 55; IMNM onset mid-40s, dysphagia in about half; anti-SRP with ILD in 41.6% of SRP-positive cases |
| del Castillo et al, 2024 [57] | Spain | Case report | Pediatric | 1 | SRP | 11-year-old girl; anti-SRP-54 + anti-Ro52; no response to steroids, then IVIG, methotrexate and rituximab; literature review of pediatric IMNM |
| Galindo-Feria et al, 2025 [33] (abstract) | Sweden/Spain | Cohort (retrospective, comparative) | Adult | 42 | HMGCR | N = 42; IV steroid (n = 12) vs no IV steroid (n = 30); CK normalization 27.2 vs 39 months (P = 0.038); high cumulative GC slowest to CK normalization; MTX and IVIG used in > 85% of both groups |
| Prieto-Pena et al, 2022 [27] | Spain | Cohort (retrospective, epidemiological) | Adult | 8 | HMGCR | N = 8; all statin-exposed; incidence 0.6/105/year, prevalence 3/105; HLA-DRB1*11 in 7/8; SLCO1B1 not associated; glucocorticoids and/or IVIG for induction (IVIG in 6), azathioprine 2, methotrexate 1 |
| Dang et al, 2025 [58] (abstract) | Vietnam | Case series | Pediatric (childhood-onset; presenting at 17 and 18 years) | 2 | HMGCR 1; HMGCR/SRP-negative, anti-Mi-2α-positive 1 | Refractory to GC + MMF/AZA; rituximab stabilized disease and CPK; delayed diagnosis 5–10 years |
| Rogers et al, 2021 [59] | USA | Case report | Adult | 1 | Seronegative | 60-year-old man, never on statins; CK 7,314; PAH; anti-HMGCR and anti-SRP negative, biopsy-diagnosed seronegative IMNM; prednisone + MMF |
| Gawey et al, 2020 [60] | USA | Case report | Adult | 1 | HMGCR | 55-year-old African-American woman; atorvastatin 4 years; IV methylprednisolone, IVIG, prednisone and methotrexate; CPK normalized at 21 weeks |
| Jayatilaka et al, 2021 [61] | USA | Case report | Adult | 1 | HMGCR | 73-year-old woman; atorvastatin 20 mg; rhabdomyolysis; prednisone, then methotrexate, then IVIG |
| Velardo et al, 2020 [25] | Italy | Case report | Pediatric | 1 | HMGCR | 7-year-old boy, initially suspected LGMD; anti-HMGCR 251.9; IV methylprednisolone, prednisone, IVIG and methotrexate |
| Zaki et al, 2021 [62] | USA | Case report | Adult | 1 | HMGCR | 67-year-old woman; atorvastatin; anti-HMGCR 150 U/mL; atypical CD4+/CD8+ infiltrate on biopsy; prednisone taper ± azathioprine; CK normalized |
| Moreira et al, 2019 [11] | Germany/multi-center | Cohort (registry) | Adult | 38 | NR (ICI-associated, not classic IMNM) | Checkpoint-inhibitor myositis/myocarditis registry; supporting evidence only |
| Fontana et al, 2024 [12] | Brazil | Cohort (diagnostic accuracy) | Mixed | 50 | Mixed (line blot incl. anti-HMGCR) | Line-blot diagnostic performance study |
| O’Grady et al, 2015 [63] | Ireland | Case report | Adult | 1 | SRP | SRP-IMNM with concurrent class III lupus nephritis; on statin; prednisolone, MMF, IV methylprednisolone, plasmapheresis, rituximab, azathioprine |
| Srivastav et al, 2026 [64] | India | Case report | Adult | 1 | HMGCR | 63-year-old woman; primary Sjogren overlap; chronic statin; anti-HMGCR + anti-Ro52; prednisolone + rituximab |
| Hama et al, 2017 [26] | Japan | Case report | Pediatric (onset age 13) | 1 | HMGCR | 24-year-old woman, onset age 13; initially diagnosed muscular dystrophy; anti-HMGCR; IV methylprednisolone, prednisolone, IVIG and MTX or tacrolimus |
| Chung et al, 2021 [13] | Korea | Cohort (multicenter, classification) | Adult | 108 | Mixed IIM (IMNM n = 1) | 2017 EULAR/ACR vs clinicoserologic classification comparison |
| Tsokkos et al, 2026 [36] | Cyprus | Cohort (retrospective) | Adult | 36 | Mixed IIM (IMNM 39%) | IMNM most frequent subtype (14/36) in this referral cohort |
| Yamaguchi et al, 2017 [65] | Japan | Case report | Adult | 1 | HMGCR | 49-year-old woman, no statin history; gastric cancer; steroid-refractory; marked improvement with IVIG |
| Itaya et al. [66] | Japan | Case report | Adult | 1 | SRP | 65-year-old man; anti-SRP; 12-year asymptomatic hyperCKemia; oral corticosteroids, then IVIG |
| Larco Rojas et al, 2015 [15] (abstract) | Spain | Cohort (retrospective) | Adult | 30 | Mixed IIM (no IMNM-specific data in abstract) | Biopsy-based cohort; antibody-histopathology associations |
| Conticini et al, 2023 [16] (Abstract) | India | Cohort (MyoCite dataset) | Adult | 250 | Mixed IIM (no IMNM-specific data in abstract) | Comorbidity profile across IIM subtypes |
| Meyer et al, 2023 [14] | Canada | Case series | Adult | 8 | Not by subtype (CTD-overlap myositis) | B-cell aggregate myopathies; supporting/overlap evidence |
| Babu et al, 2015 [17] | USA | Narrative review | Adult | NR | HMGCR | Early SINAM review, background/mechanistic |
| Meyer, 2023 [18] | France | Narrative review | NR | NR | NR | French-language review of inflammatory myopathies (broad IIM update) |
| Baah et al, 2021 [67] | USA | Case report | Adult (young, 29 years) | 1 | SRP | 29-year-old man; anti-SRP NAM; NSIP progressing to UIP + PAH; prednisone + MMF; bilateral lung transplant |
| Esmail, 2019 [68] (abstract) | UK | Case report | Adult | 1 | HMGCR (IMNM + IBM overlap) | 69-year-old man; CK 4,935; strongly anti-HMGCR positive; dual IMNM/IBM histology, deep-finger-flexor sparing; excellent response to steroid + azathioprine |
| Caballero et al, 2025 [31] (abstract) | Spain | Cohort (histopathology) | Adult | 140 | HMGCR 20, SRP 10 (IMNM subset of 30) | 140 biopsies; IMNM 30 (HMGCR 20, SRP 10); lipid droplets 18/20 HMGCR (90%), 3/10 SRP vs 8.3% (10/120) other antibodies, P < 0.001 |
| Nishimura et al, 2024 [69] | Germany | Cohort (morphometric/transcriptomic) | Adult | 59 | Mixed IIM (IMNM n = 7) | IIM n = 33 (IMNM 7); MHC-1, MHC-2, ICAM-1 quantification; ICAM-1 on myofibers higher in IMNM than controls, MHC-1 lower in IMNM than ASyS/DM/IBM |
| Knapp et al, 2025 [70] (abstract) | USA | Case report | Adult | 1 | Seronegative | 75-year-old man, 1 month post-CABG on atorvastatin; CK > 80,000, ANA 1:320; anti-HMGCR/SRP negative; fatal course; IVIG and pulse methylprednisolone given |
| Mekmangkonthong et al, 2022 [71] | Thailand | Case report | Pediatric | 1 | HMGCR | 9-year-old boy; dengue-triggered; anti-HMGCR; prednisolone, six monthly IVIG cycles, then methotrexate; complete recovery |
| Xiong et al, 2021 [23] | China | Systematic review of cases | Mixed (11–81 years) | 34 | SRP 18/34 (52.9%), HMGCR 16/34 (47.1%) | N = 34 (SRP 18/34, HMGCR 16/34); mean age 41 years; 61.8% responded to RTX after failure of steroids + IS; all received high-dose steroids before RTX |
| Tanaka et al, 2026 [72] | Japan | Case series | Adult | 2 | SRP | 2 patients (68-year man, 67-year woman); anti-SRP IMNM with Sjogren disease; relatively mild weakness and better response to immunotherapy than typical IMNM; severe Raynaud phenomenon in one |
| Kato et al, 2025 [73] | Japan | Case report | Pediatric | 1 | SRP (19/68/72 kDa subunits) | 9-year-old girl; routine MSA panel negative, anti-SRP subunits 19/68/72 kDa positive; initially diagnosed JDM/FSHD; methylprednisolone, prednisolone, MTX, MMF, IV cyclophosphamide, tacrolimus |
| Zeng et al, 2024 [74] | China | Case report | Adult | 1 | HMGCR | 66-year-old man; refractory to high-dose glucocorticoid + IVIG; rapid improvement after 1 cycle of efgartigimod; discharged on prednisone + MMF |
| Yerolatsite et al, 2025 [75] | Greece | Case series + literature review | Adult | 5 | HMGCR 4, SRP 1 | N = 5 (4 HMGCR/1 SRP); all steroids, 4/5 second-line (IVIG, MTX, AZA, MMF); PCSK9i safe, no relapse; CPK 1,028 to 135, LDL 206 to 87; literature review n = 15 |
| Dinh et al, 2026 [29] | USA | Cohort (retrospective) | Adult | 148 | HMGCR (46.9% NA vs 16.5% non-NA) | N = 148 IIM (33 NA); anti-HMGCR 46.9% NA vs 16.5% non-NA (P = 0.0007); statin exposure 71.9% vs 40.0%; prevalence 182 vs 30.6/106; incidence 66.4 vs 7.5/106/year; outcomes and treatment similar |
| Kurashige et al, 2024 [39] | Japan | Cohort (retrospective) | Adult | 100 | HMGCR (19 with IMNM) | N = 100 IIM; any skin condition 34 (34%); atypical neck/back skin lesions in 8/19 (42%) HMGCR-IMNM vs none in other IIM (P < 0.001); Bcl-2+ lymphocytic infiltrate in skin and muscle |
| Qin et al, 2024 [76] | China | Case report | Adult | 1 | SRP | Anti-BCMA CAR-T for refractory disease (prior IVIG, prednisone, tocilizumab); single-cell analysis |
| Huo et al, 2026 [37] | China | Cohort (treatment-naive) | Adult | 28 | Not by subtype | 28 treatment-naive IMNM vs 25 healthy controls; IL-6, IFN-γ, IgG, IgM, B cells and CD8+ T cells increased; CD4+ T cells and NK cells decreased |
| Gao et al, 2026 [77] | China | Cohort (mechanistic/biomarker) | Adult | NR | Seropositive and seronegative IMNM | pMLKL expressed in 93.5% of IMNM vs 50% other IIM and 47.9% non-IIM myopathies (P < 0.0001); seropositive and seronegative IMNM; Huashan Hospital |
| Bienz et al, 2025 [78] | Switzerland | Case report | Adult | 1 | Seronegative | Cardio-renal (Pickering syndrome) complication; prednisolone + azathioprine |
| Garabet et al, 2024 [79] | USA | Case report | Adult | 1 | HMGCR + AChR (overlap) | 67-year-old man; atorvastatin; flaccid paralysis and respiratory failure; CK 24,000; anti-HMGCR and anti-AChR increased; methylprednisolone, IVIG and rituximab |
| Hayashi et al, 2024 [80] | Japan | Case report | Adult | 1 | Seronegative | Onset during pregnancy; treated immediately with systemic corticosteroids with improvement and no adverse pregnancy effect |
| Study | Population/setting | N | Reported patient-level data | Typea |
|---|---|---|---|---|
| aType: Full = full-length article; Abstract = conference/congress abstract. IIM: idiopathic inflammatory myopathy; SMR: standardized mortality ratio; HMGCR: 3-hydroxy-3-methylglutaryl-coenzyme A reductase; ECG: electrocardiogram; CK: creatine kinase; CPK: creatine phosphokinase; LDL: low-density lipoprotein; IV: intravenous; SRP: signal recognition particle; PCSK9: proprotein convertase subtilisin/kexin type 9; IMNM: immune-mediated necrotizing myopathy; RCT: randomized controlled trial. | ||||
| Chen et al, 2025 [35] | Adult IIM, China, multicenter retrospective | 216 IMNM (of 1,854 IIM) | Anti-SRP 51.4%, anti-HMGCR 28.2%, seronegative 20.4%; IMNM SMR 2.74 (anti-SRP 4.12) | Full |
| Wang et al, 2025 [24] | Pediatric, single-center | 55 | Anti-HMGCR 61.8%, anti-SRP 20.0%, seronegative 18.2%; complete or partial remission 18/39 (46.2%) of patients followed up | Full |
| Pongtarakulpanit et al, 2025 [42] | Adult IIM registry, USA | 45 IMNM (of 440) | Remission 26.7% (12/45) | Abstract |
| Martinez-Lopez et al, 2023 [32] | Anti-HMGCR, multicenter retrospective | 24 | Remission or low disease activity 21/24 (87.5%), including all 5 on a glucocorticoid-free IVIG-based regimen; 3/19 glucocorticoid-treated not in remission | Abstract |
| Galindo-Feria et al, 2025 [33] | Anti-HMGCR, IV steroid (n = 12) vs no IV steroid (n = 30), Sweden/Spain | 42 | CK normalization 27.2 vs 39 months (P = 0.038) favoring no IV steroids; high cumulative glucocorticoid dose associated with slowest normalization | Abstract |
| Xiong et al, 2021 [23] | Pooled published cases, rituximab | 34 | Anti-SRP 52.9%, anti-HMGCR 47.1%; 61.8% responded to rituximab | Full |
| Sumi et al, 2025 [38] | Adult, cardiac involvement, Japan | 13 | All with elevated troponin T; 76.9% ECG/echo abnormal; 23.1% acute heart failure (1 death); anti-Kv1.4 positive 83.3% | Full |
| Kurashige et al, 2024 [39] | IIM, Japan | 100 IIM (19 HMGCR-IMNM) | Atypical neck/back skin lesions in 8/19 (42%) HMGCR-IMNM versus none in other IIM (P < 0.001); any skin condition in 34/100 (34%) | Full |
| Aziz et al, 2025 [28] | Myositis clinic, UK | 31 | Anti-HMGCR 7/31 (22.6%), all statin-exposed; 6/7 clinical IMNM phenotype | Abstract |
| Prieto-Pena et al, 2022 [27] | Anti-HMGCR, northern Spain | 8 | All statin-exposed; HLA-DRB1*11 in 7/8 (87.5%) | Full |
| Dinh et al, 2026 [29] | IIM, USA, Native American versus other | 148 IIM (33 Native American) | Anti-HMGCR 46.9% versus 16.5% (P = 0.0007); prevalence 182 versus 30.6 and incidence 66.4 versus 7.5 per 106 | Full |
| Tsokkos et al, 2026 [36] | IIM referral center, Cyprus | 36 IIM | IMNM 14/36 (39%), most frequent subtype | Full |
| Caballero et al. [31] | Muscle biopsies, Spain | 140 IIM (30 IMNM) | Lipid droplets in 90% of anti-HMGCR biopsies versus 8.3% of other antibody subtypes (P < 0.001) | Abstract |
| Yerolatsite et al, 2025 [75] | Anti-HMGCR/SRP on PCSK9 inhibitor | 5 (plus 15 from literature) | PCSK9 inhibitors safe, no relapse; CPK 1,028 to 135, LDL 206 to 87 | Full |
| Huo et al. [37] | Treatment-naive IMNM, China | 28 | Peripheral immune profiling versus 25 healthy controls (no clinical-outcome estimate) | Full |
| Mammen et al, 2023 [34] | Phase 2 RCT, zilucoplan versus placebo, 8 weeks | 27 | Primary CK endpoint not met (P = 0.46); 12 in zilucoplan group, 15 in placebo group | Full |