Balanced Crystalloids Versus Normal Saline for Fluid Resuscitation in Pediatric Septic Shock: An Updated Systematic Review and Meta-Analysis
DOI:
https://doi.org/10.14740/jocmr6685Keywords:
Balanced crystalloids, Normal saline, Pediatric sepsis, Septic shock, Acute kidney injury, Hyperchloremia, Meta-analysisAbstract
Background: Crystalloid fluid is central to pediatric septic shock resuscitation, but the optimal composition is uncertain. Normal saline delivers a supraphysiologic chloride load that may promote hyperchloremic acidosis and renal injury, whereas balanced crystalloids approximate extracellular fluid. Pediatric evidence is mixed, and prior syntheses preceded the large PRoMPT BOLUS trial. We compared balanced crystalloids with normal saline for resuscitation in children with sepsis or septic shock.
Methods: We searched PubMed/MEDLINE, Scopus, Web of Science, and Cochrane Central Register of Controlled Trials (CENTRAL) from inception to April 2026 for randomized controlled trials (RCTs) and observational cohorts comparing balanced crystalloids with 0.9% saline in children (≤ 18 years) with sepsis or septic shock requiring fluid resuscitation. Co-primary outcomes were all-cause mortality and acute kidney injury (AKI). Data were pooled using random-effects models (risk ratios (RR), mean differences (MD); 95% confidence interval (CI)), with trial sequential analysis (TSA) for primary outcomes. The review followed the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) 2020 and was registered in PROSPERO.
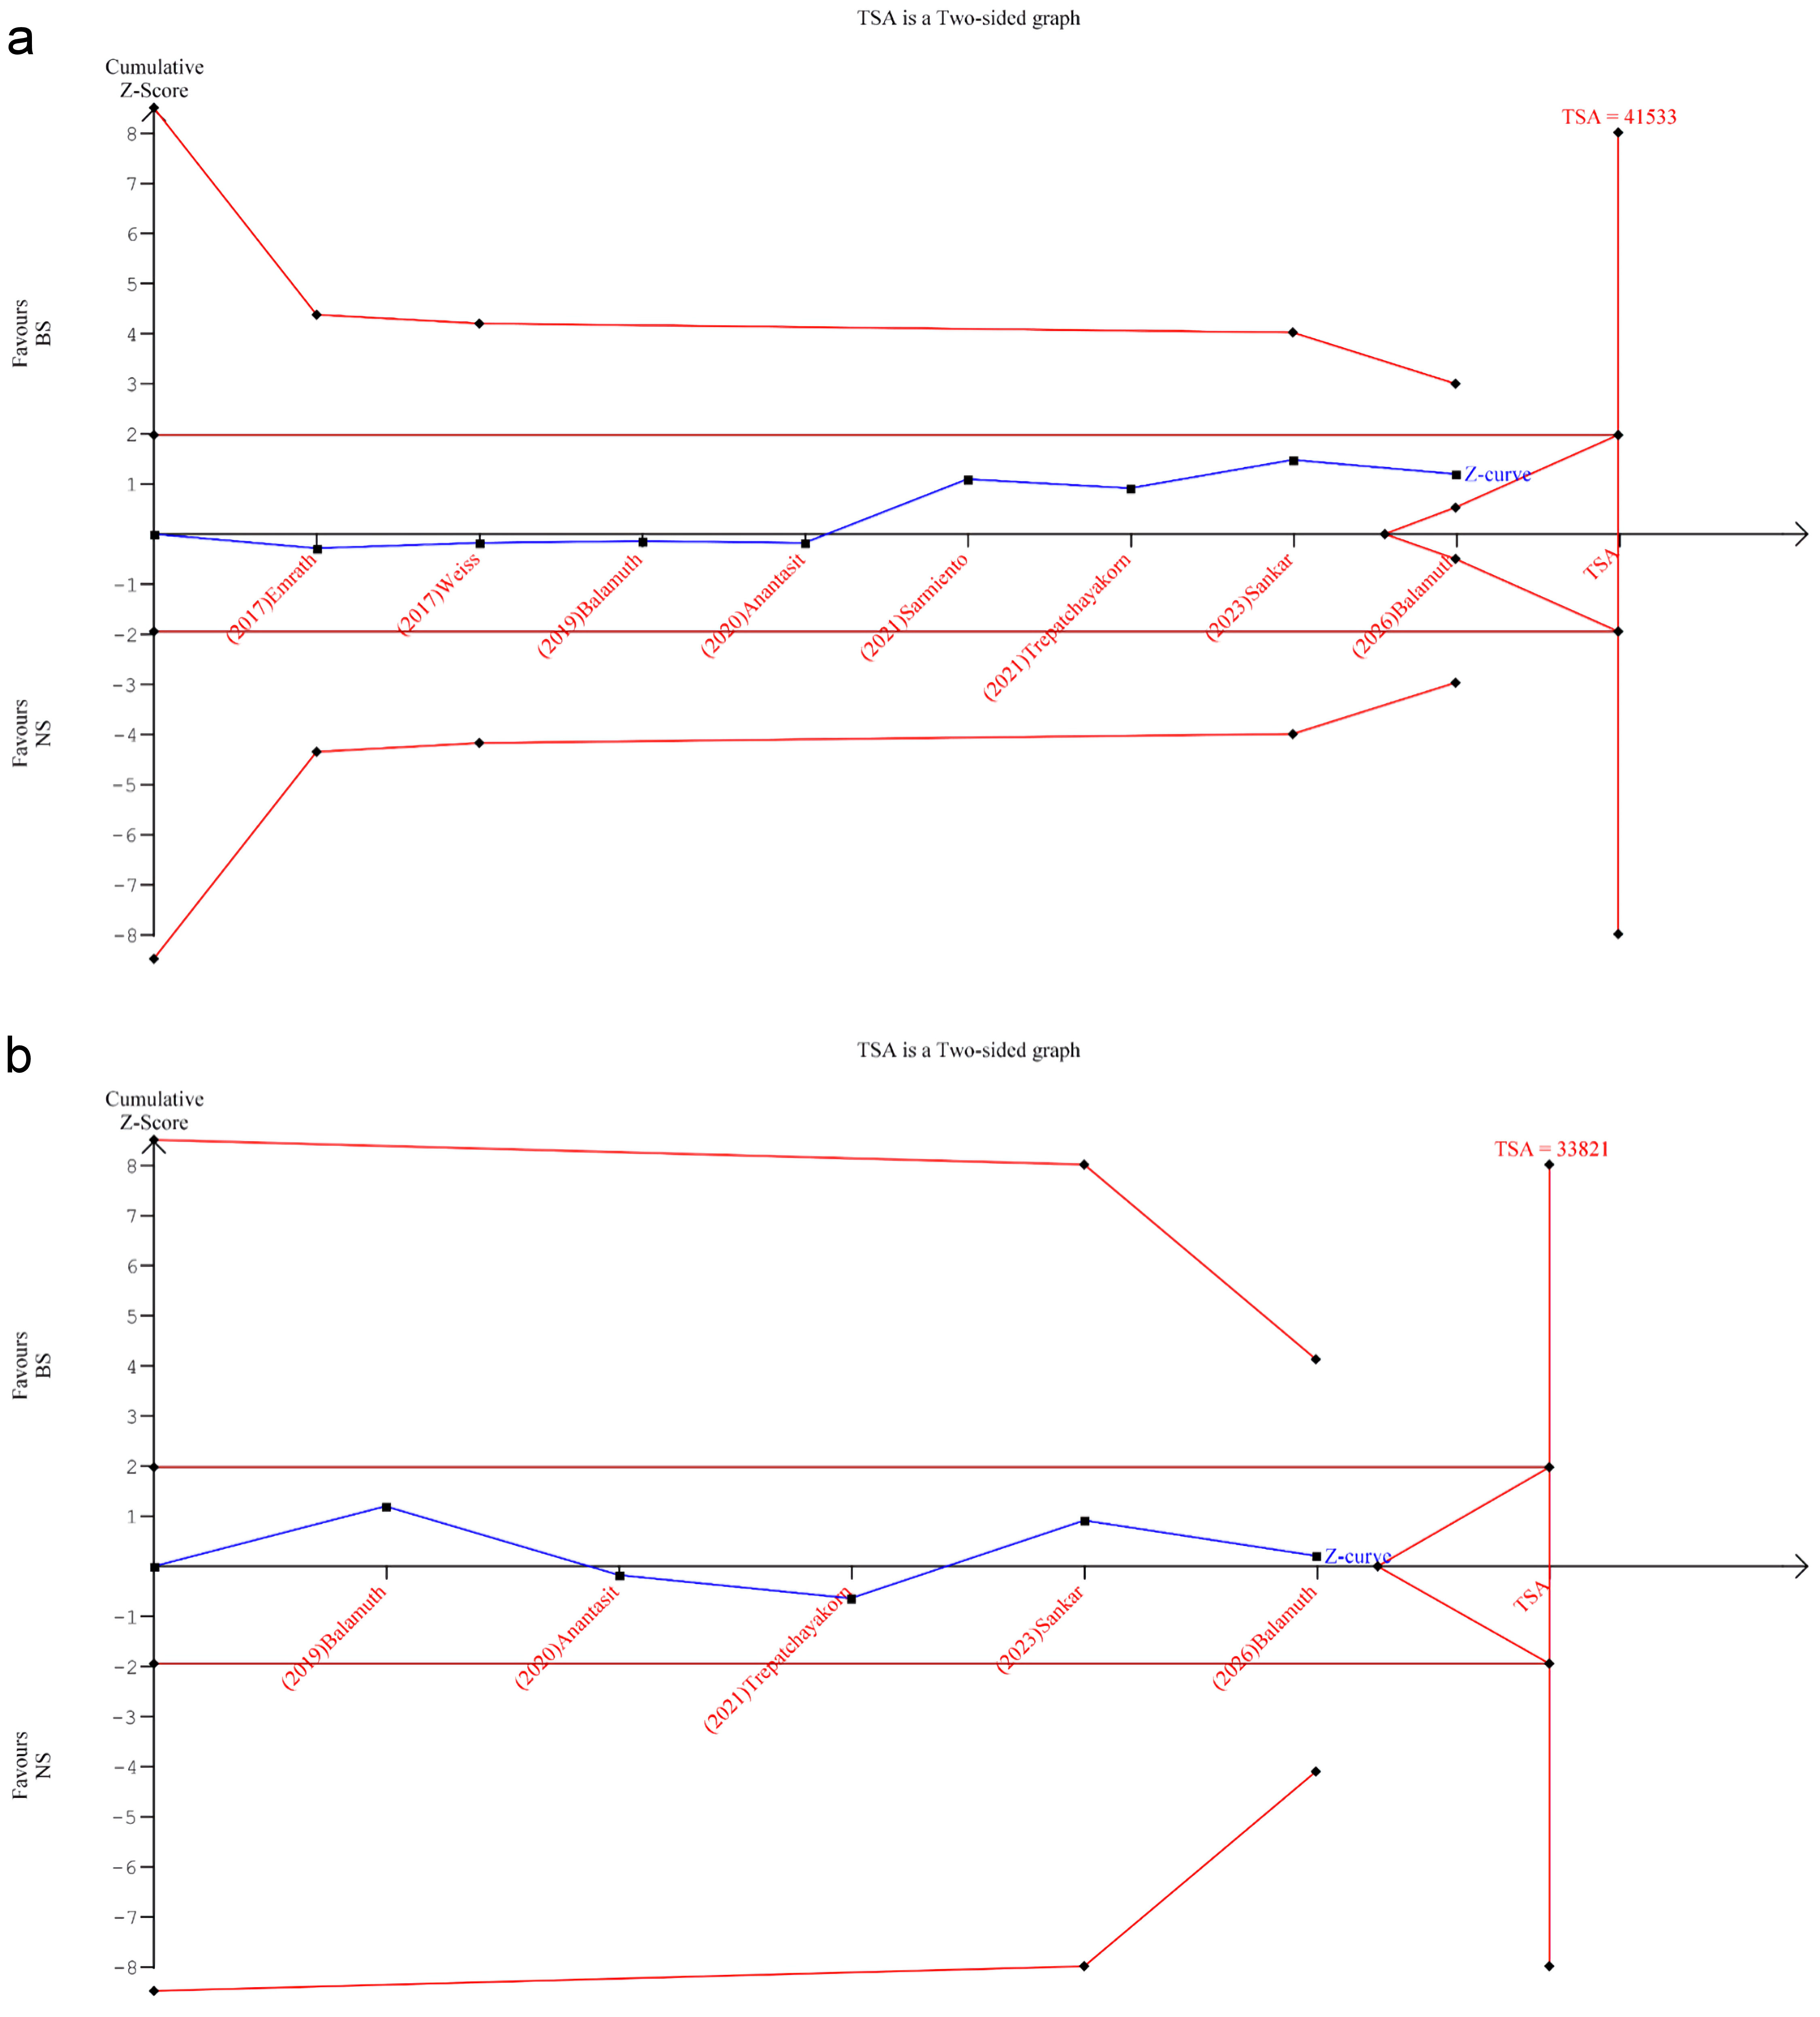
Results: Nine studies (five RCTs, four observational cohorts) were included. Balanced crystalloids did not reduce mortality (RR, 0.94; 95% CI, 0.83–1.06; I2 = 0%) or AKI (RR, 0.84; 95% CI, 0.61–1.16; I2 = 73.5%); TSA showed the required information size was unmet, leaving both inconclusive. Balanced crystalloids significantly reduced renal replacement therapy (RR 0.74; 95% CI, 0.56–0.96; I2 = 23.5%) and hyperchloremia (RR, 0.65; 95% CI, 0.61–0.69; I2 = 0%). No differences emerged for major adverse kidney events within 30 days (MAKE30) (RR, 1.11; 95% CI, 0.87–1.41), mechanical ventilation (RR, 0.97, 95% CI, 0.85–1.11), or hospital (MD, 1.49 days) and pediatric intensive care unit (PICU) (MD, 0.84 days) length of stay.
Conclusions: In pediatric sepsis or septic shock, balanced crystalloids consistently reduce hyperchloremia and the need for renal replacement therapy but do not significantly reduce mortality, AKI, MAKE30, mechanical ventilation, or length of stay. Incorporating recent pragmatic randomized data supports cautious interpretation, and TSA confirms that the primary-outcome evidence remains inconclusive. Adequately powered, phenotype-informed trials are needed.
Published
Issue
Section
License
Copyright (c) 2026 The authors

This work is licensed under a Creative Commons Attribution 4.0 International License.